
 Want to earn continuing education credit for this article? Learn more.
Iliotibial band (ITB) syndrome is recognized as one of the most common lower-extremity injuries in athletes, especially in long-distance runners and cyclists. Casually referred to as runner’s knee, massage therapists are likely to encounter this overuse condition.
Researchers have proposed different explanations for ITB syndrome. Traditionally, the condition was attributed to excessive friction between the ITB and the lateral femoral epicondyle. However, anatomical research suggests that compression of sensitive tissues beneath the ITB may play a more significant role. Impaired hip muscle function and altered lower-extremity biomechanics may also contribute to the condition. Although its exact causes remain under investigation, several conservative treatment approaches, including bodywork, may help manage symptoms.
About ITB Syndrome
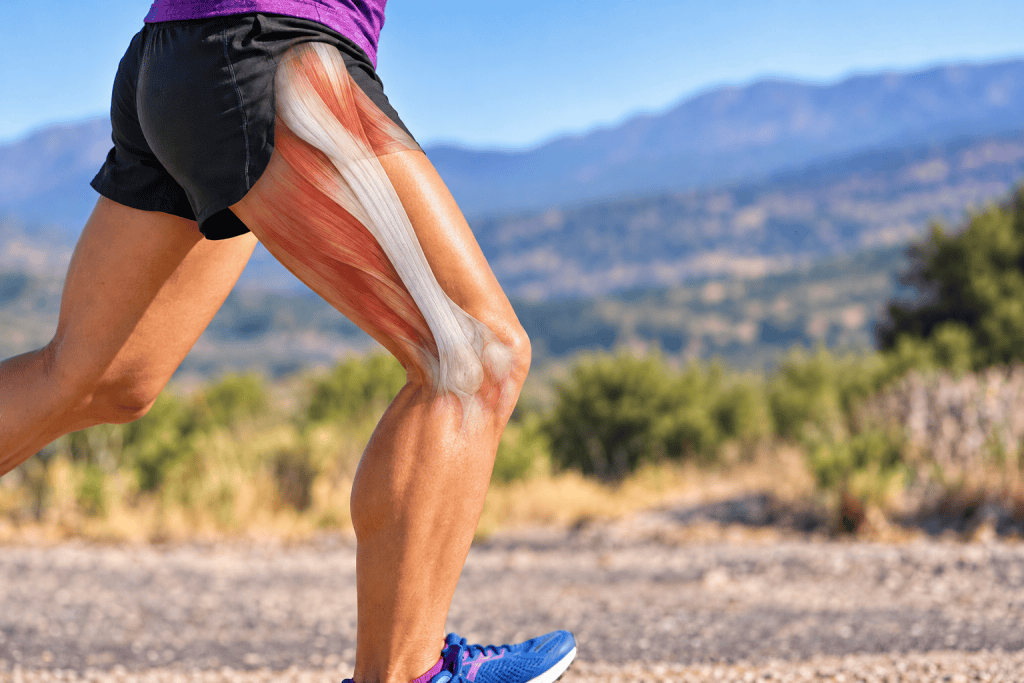
ITB syndrome is often observed in those who exercise vigorously. The iliotibial band is a thickened portion of fascia extending along the outside of the thigh from the hip to the lateral knee. During knee flexion and extension, tension changes within the ITB. Rather than repeatedly rubbing across the lateral femoral epicondyle, as traditionally believed, the ITB appears to compress the underlying tissues, potentially contributing to pain and irritation.
In runners, symptoms often occur when the knee is flexed approximately 20 to 30 degrees during the stance phase of running. Downhill running may aggravate ITB syndrome because of changes in knee position and loading. Symptoms may also be influenced by running speed, training volume and individual biomechanics.
While the most prevalent symptom of ITB syndrome is lateral knee pain, other signs may include:
- Hip pain or discomfort along the outside of the thigh.
- Discomfort, which may radiate from the knee proximally or distally.
- Pain during strenuous activity; however, a case that has progressed may cause pain with walking.
- A tender point near the lateral femoral epicondyle.
- Pain elicited with active flexion-extension of the knee within the first 30 degrees, while pressure is applied near the lateral femoral epicondyle. This finding may assist a qualified healthcare professional in evaluating ITB syndrome but is not sufficient for diagnosis on its own.
ITB Syndrome Causes
Even though there is little scientific support of ITB syndrome’s etiology, experts agree that it has many possible causes. In addition to an athletic injury associated with changes in running surface, speed, distance or footwear, the following factors have been investigated for their possible contributions to ITB syndrome:
- Limb length discrepancy
- Bow-leggedness (Genu varum)
- Over-pronation
- Hip abductor weakness or impaired hip muscle control
- Altered running mechanics and lower-extremity movement patterns
Treatment
The basic principles of treating ITB syndrome are similar to any soft tissue injury. Conservative treatment generally focuses on reducing symptoms, modifying aggravating activities and addressing contributing biomechanical factors. The following strategies may help athletes with ITB syndrome return to their sport:
- Symptom management, with ice used for temporary pain relief if desired rather than as a treatment proven to accelerate healing
- Activity modification by avoiding or temporarily reducing aggravating motions
- Addressing underlying biomechanical factors through appropriate assessment and rehabilitation
- Progressive strengthening exercises, particularly for the hip abductors and other muscles involved in lower-extremity stability
- Gradual return to activity as symptoms improve
A 2024 systematic review examining conservative treatments for ITB syndrome found that hip abductor strengthening was a common component of successful rehabilitation programs. Manual therapy may provide additional benefits when combined with exercise, although more research is needed to determine the most effective treatment approaches.
Additionally, bodywork may help reduce discomfort and improve movement tolerance when incorporated into a broader rehabilitation program.
In Clinical Application of Neuromuscular Techniques, Leon Chaitow and Judith Walker DeLany describe four techniques traditionally used to address tension in the iliotibial band:
- Along the tensor fascia latae, apply short gliding strokes, friction and static compression.
- Along the ITB, apply lubricated gliding strokes.
- For a shortened or fibrotic iliotibial band, apply a myofascial release technique that imitates a twig snapping motion.
- To release a hypertonic, shortened iliotibial band, create an alternating sequence by using the heel of one hand to alternately thrust against the IT band, while stabilizing it with the other hand.
Although these techniques have traditionally been used in neuromuscular therapy, current research does not establish that massage can physically lengthen or release the ITB. Deep or aggressive pressure over painful tissues, particularly near the lateral knee, may aggravate symptoms. Massage therapists should adjust techniques according to client tolerance and consider massage an adjunct to appropriate rehabilitation rather than a stand-alone treatment.
Aside from myofascial release and neuromuscular therapy, strain-counterstrain has also been described as a treatment for ITB syndrome. As published in the December 2005 edition of The Journal of the American Osteopathic Association, moving the lower limb into a position of greatest comfort and then applying the osteopathic counterstrain technique was associated with pain relief in a single case report involving a distance runner. Although the findings were encouraging, a single case report cannot establish the effectiveness of this technique for ITB syndrome.
More recent research suggests that manual therapy may help reduce pain and improve function, particularly when combined with strengthening exercises and other rehabilitation strategies. However, the available evidence remains limited, and no single massage technique has been established as the most effective approach.
Despite its commonality in runners and cyclists, the ambiguity regarding ITB syndrome’s origins renders it a challenge for many health practitioners. However, incorporating massage therapy into a treatment plan that includes activity modification, progressive strengthening and correction of contributing biomechanical factors may help clients manage discomfort and return to activity. In particular, familiarity with neuromuscular therapy, myofascial release and other gentle manual techniques may provide massage therapists with useful options for supporting clients experiencing ITB syndrome.
Originally posted March 2011. Updated October 28, 2026.
Earn continuing education credit for this article contained in our Common Sports Injuries series. Click here to enroll.

 Follow Us